 MATEO ZAPATA
Care Model
In a gastroenterology clinic, quality cannot live only in protocols on the wall. If nobody evaluates the care model — roles, categories, hand hygiene — compliance becomes anecdote and leadership finds the gaps late. The pain: scattered care auditing with no executive reading. SAM turns the Care Model into a living quality system.
Role-based evaluations
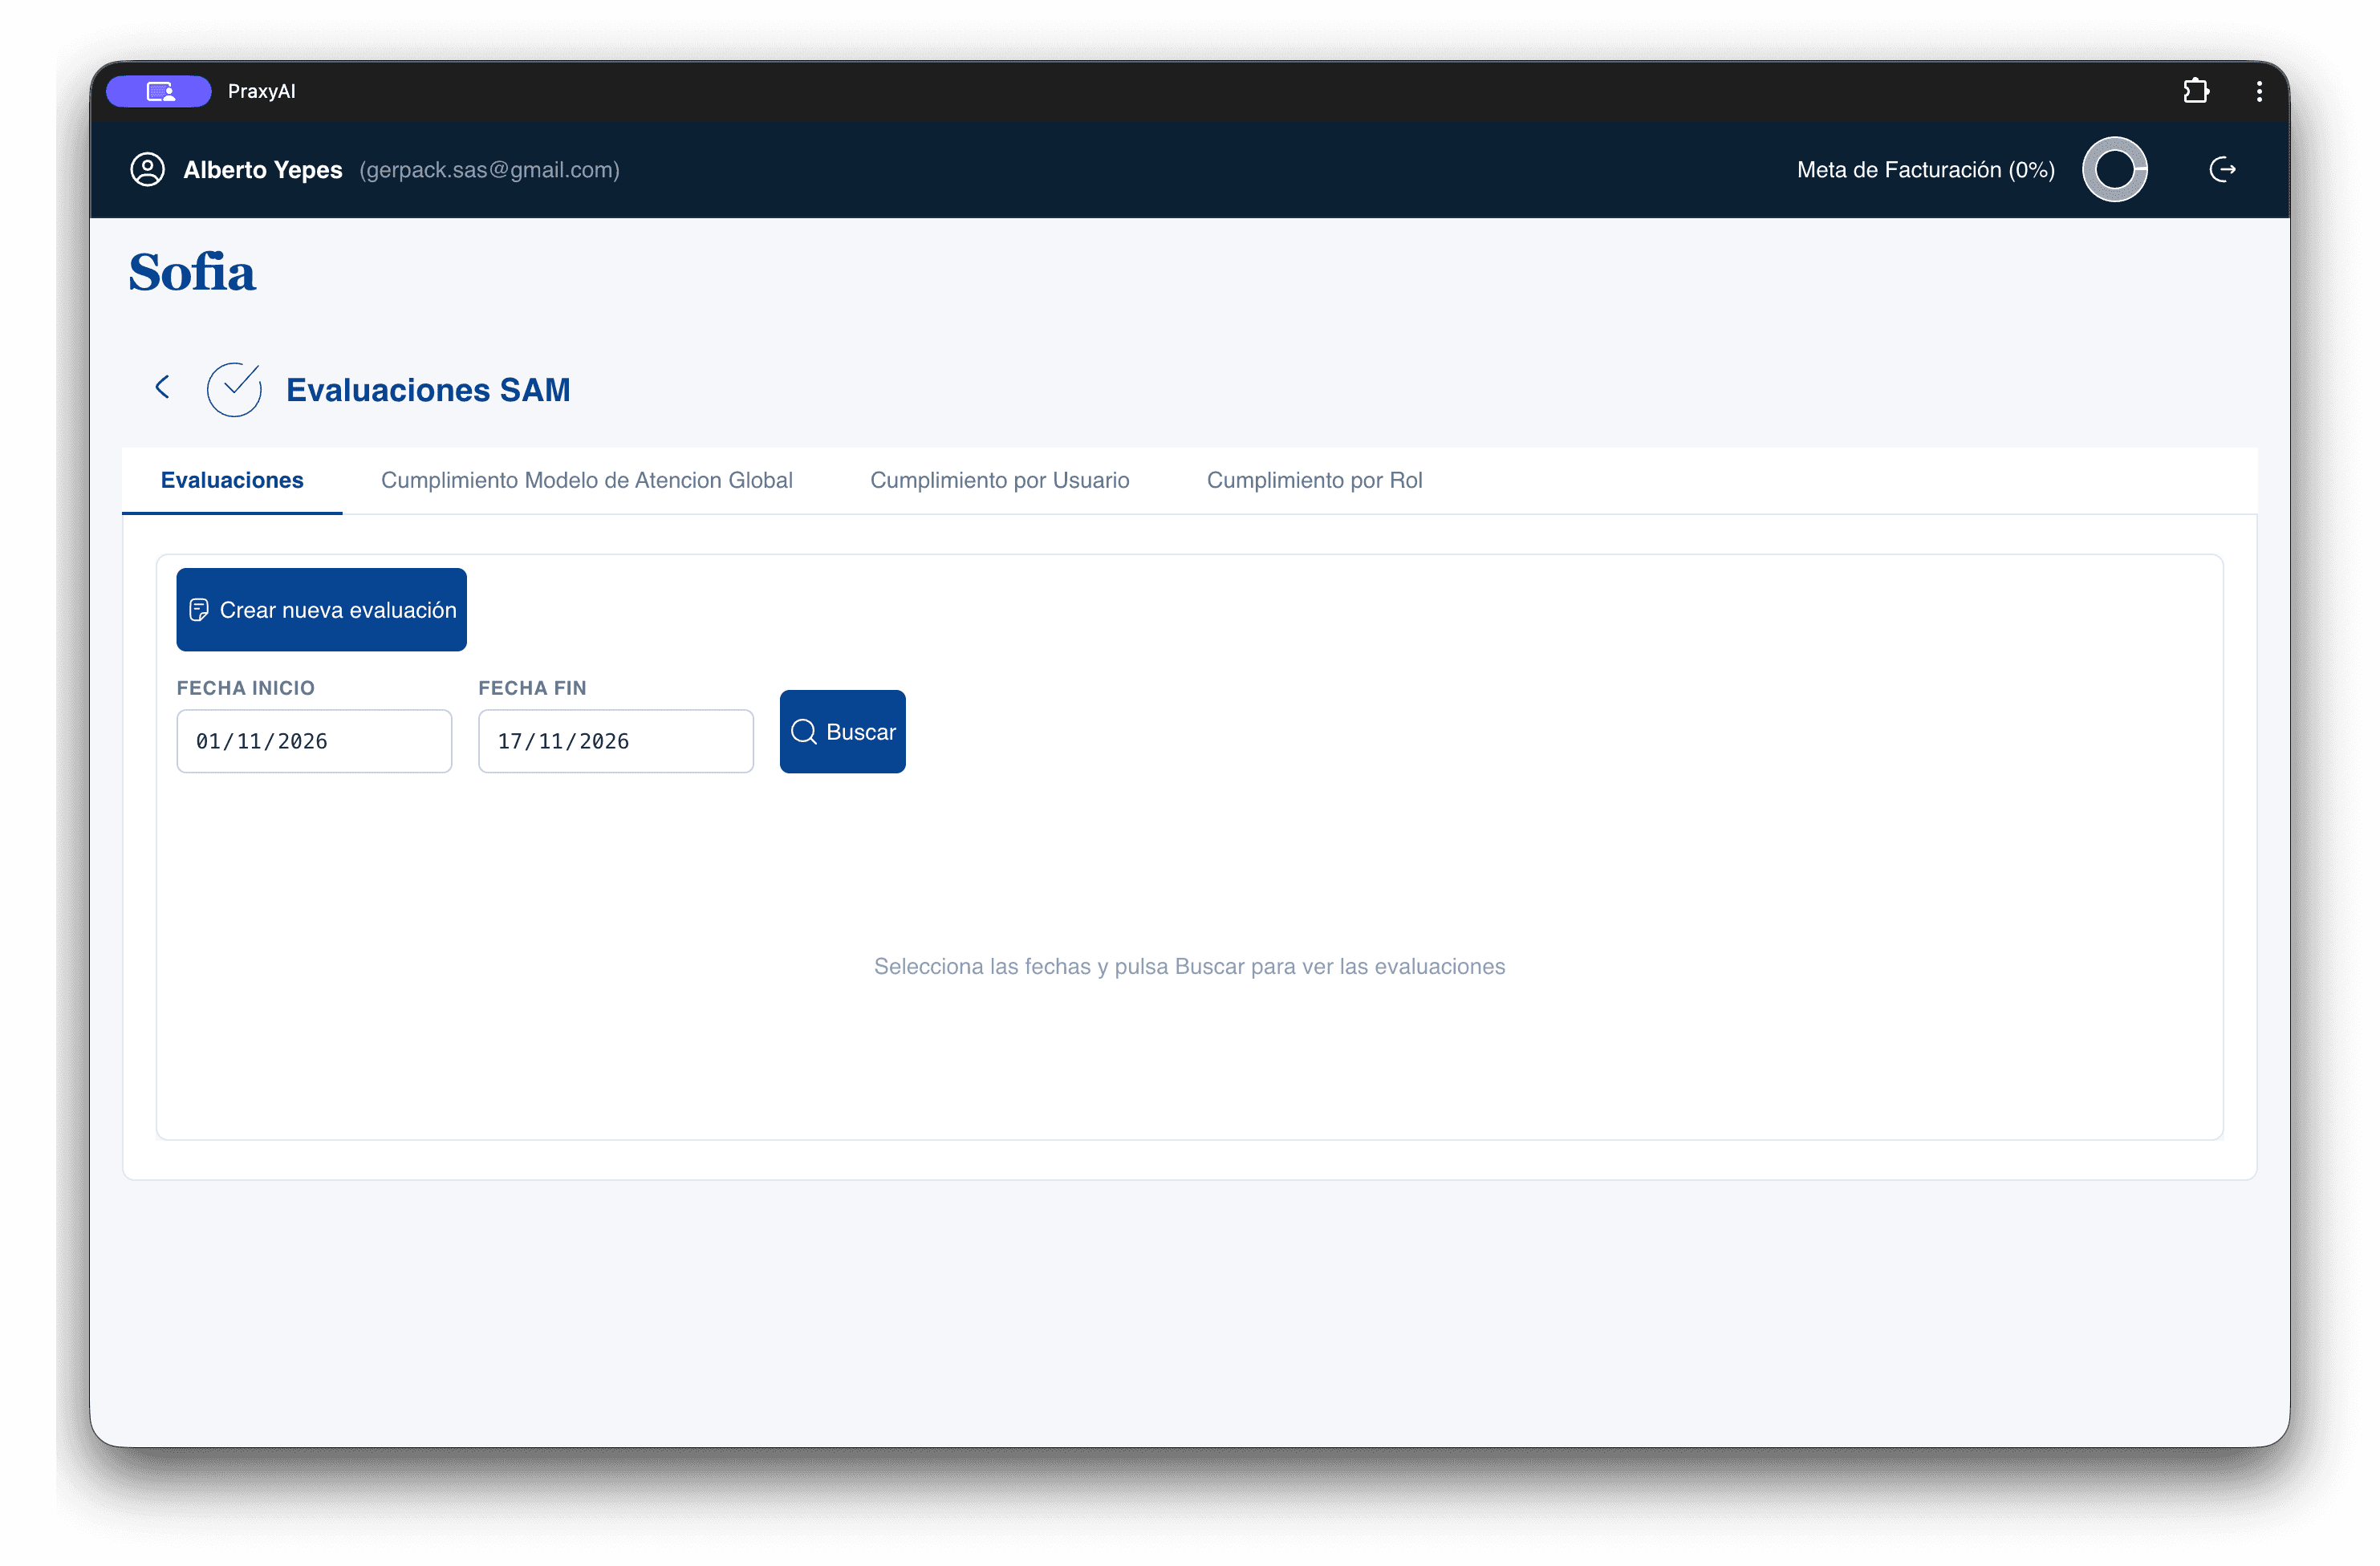
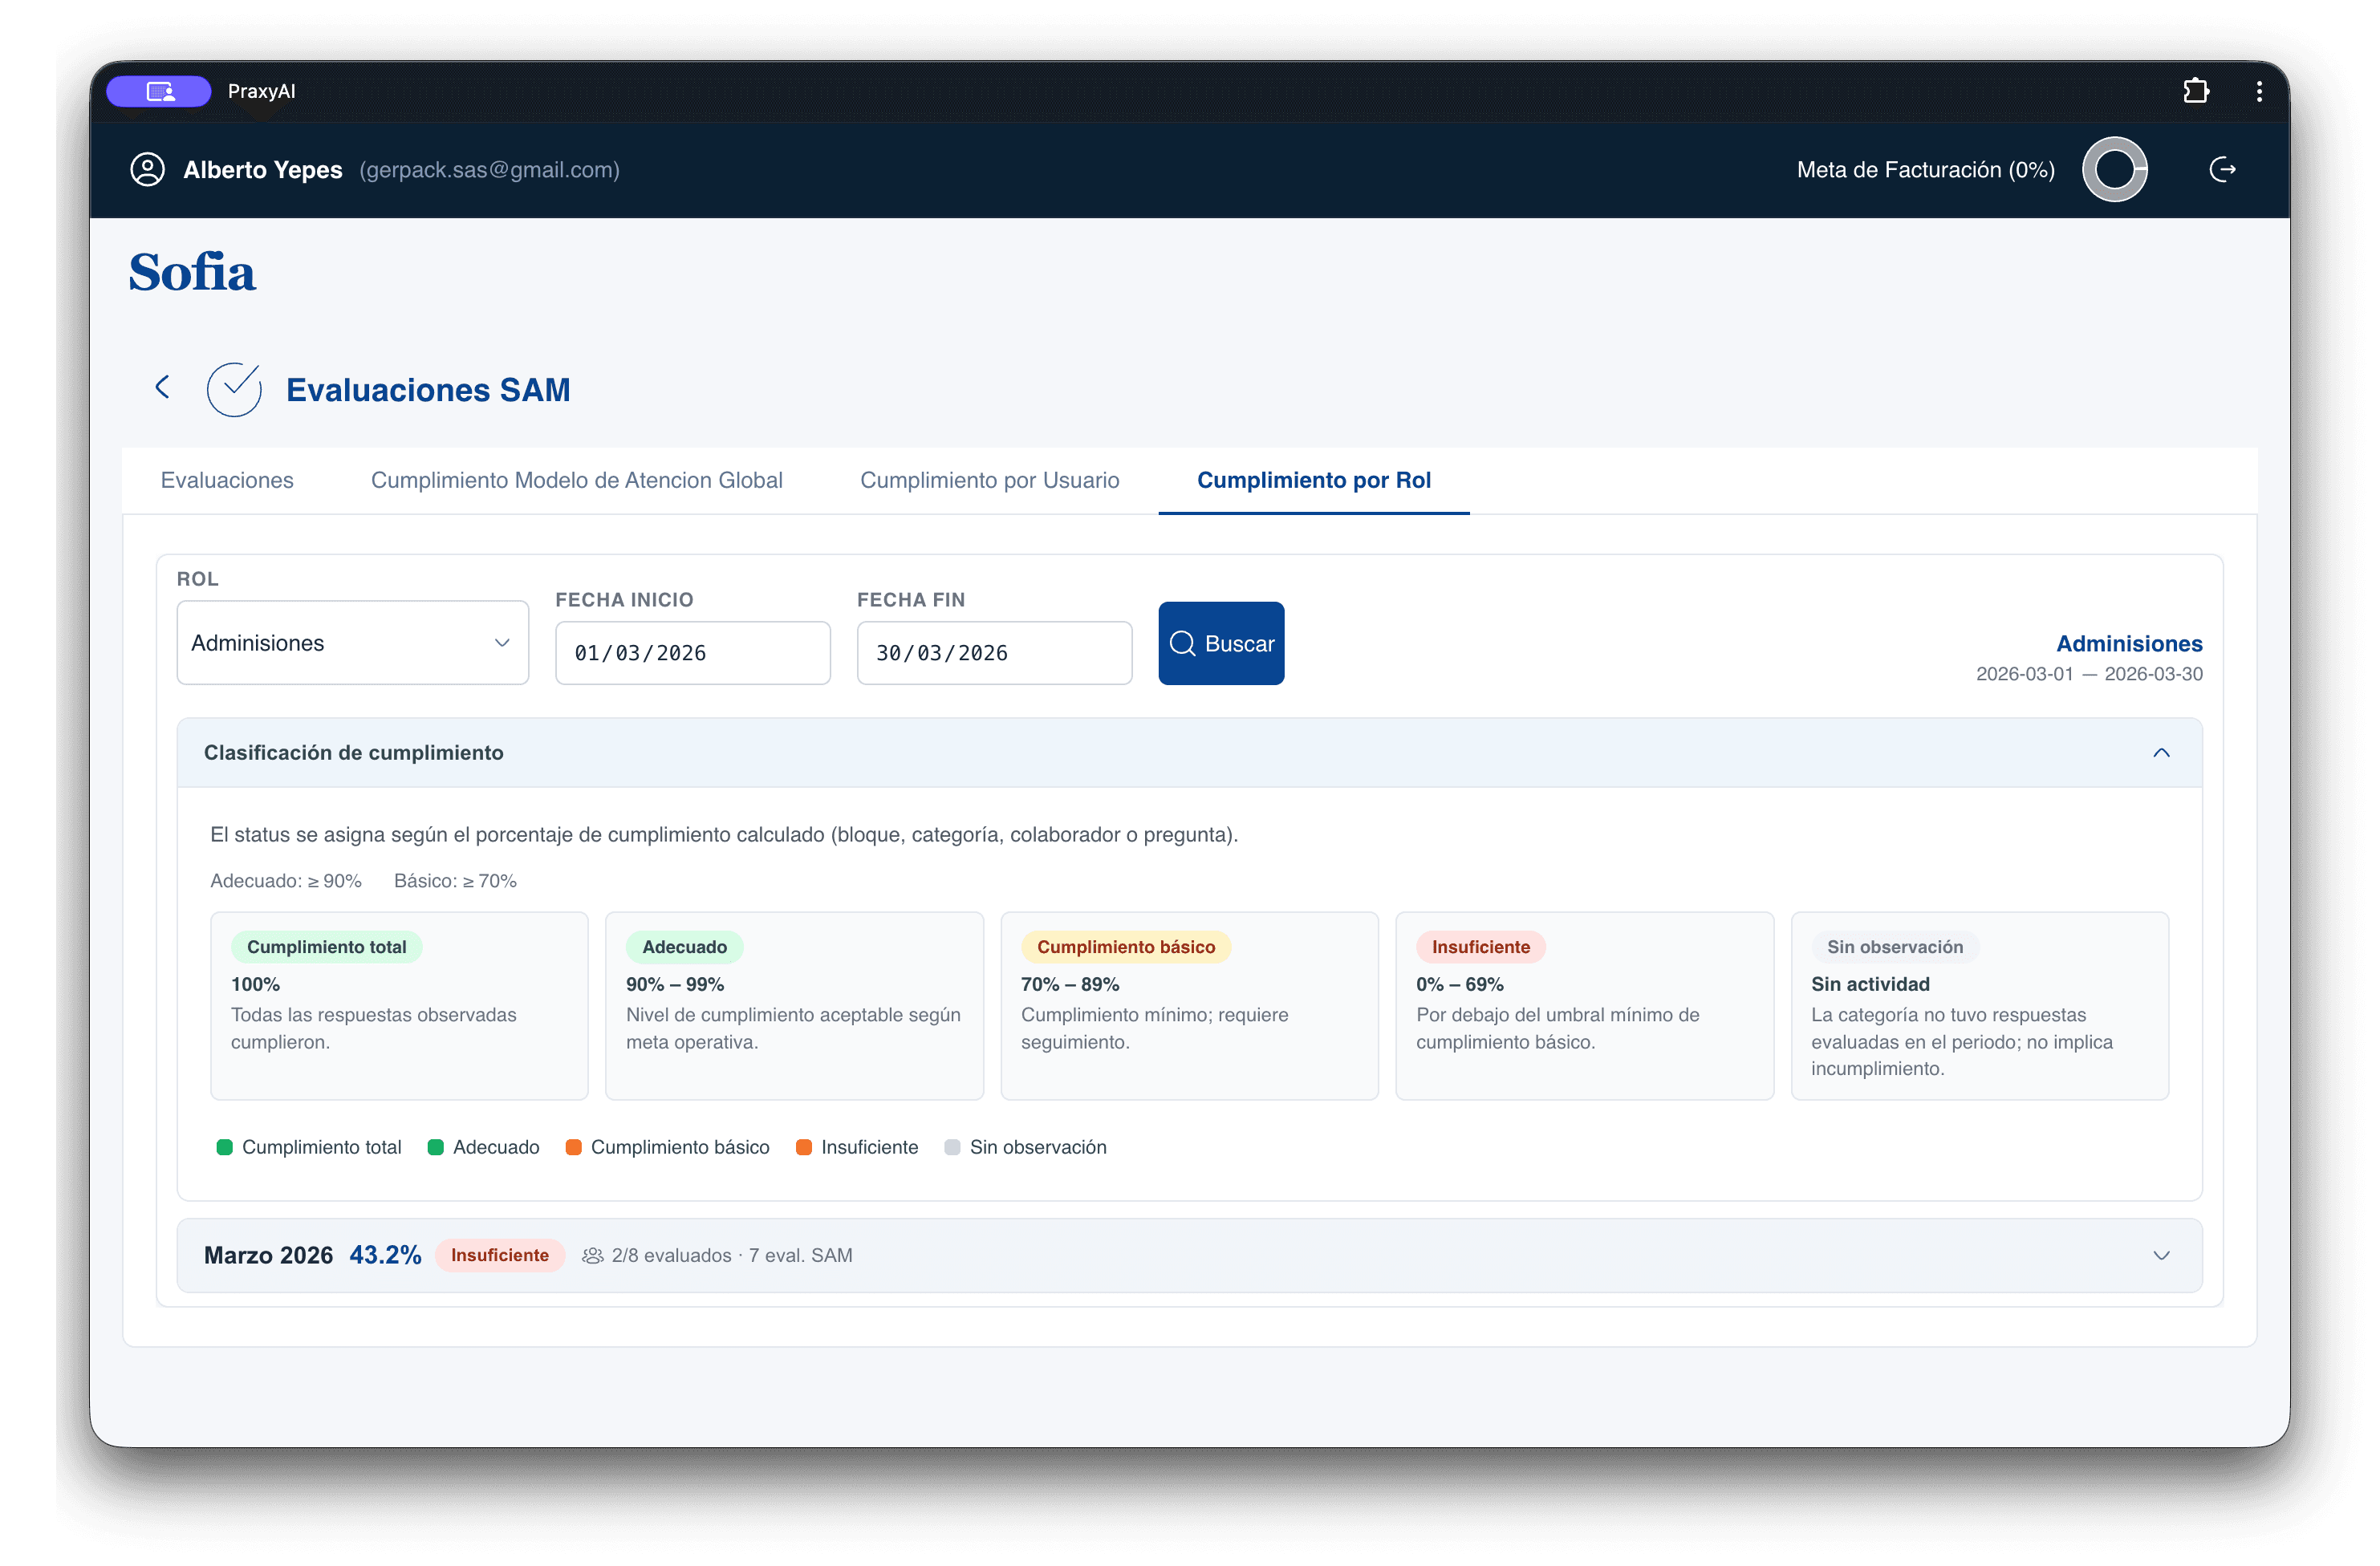
You create evaluations by role and see who was assessed. The model stops being a wall protocol and becomes an audit assigned to real operations.
Category questionnaires
You answer by category — reception, phone, cancellation, confirmation, and more. You measure real model compliance, not the intent of the document.
Hand hygiene
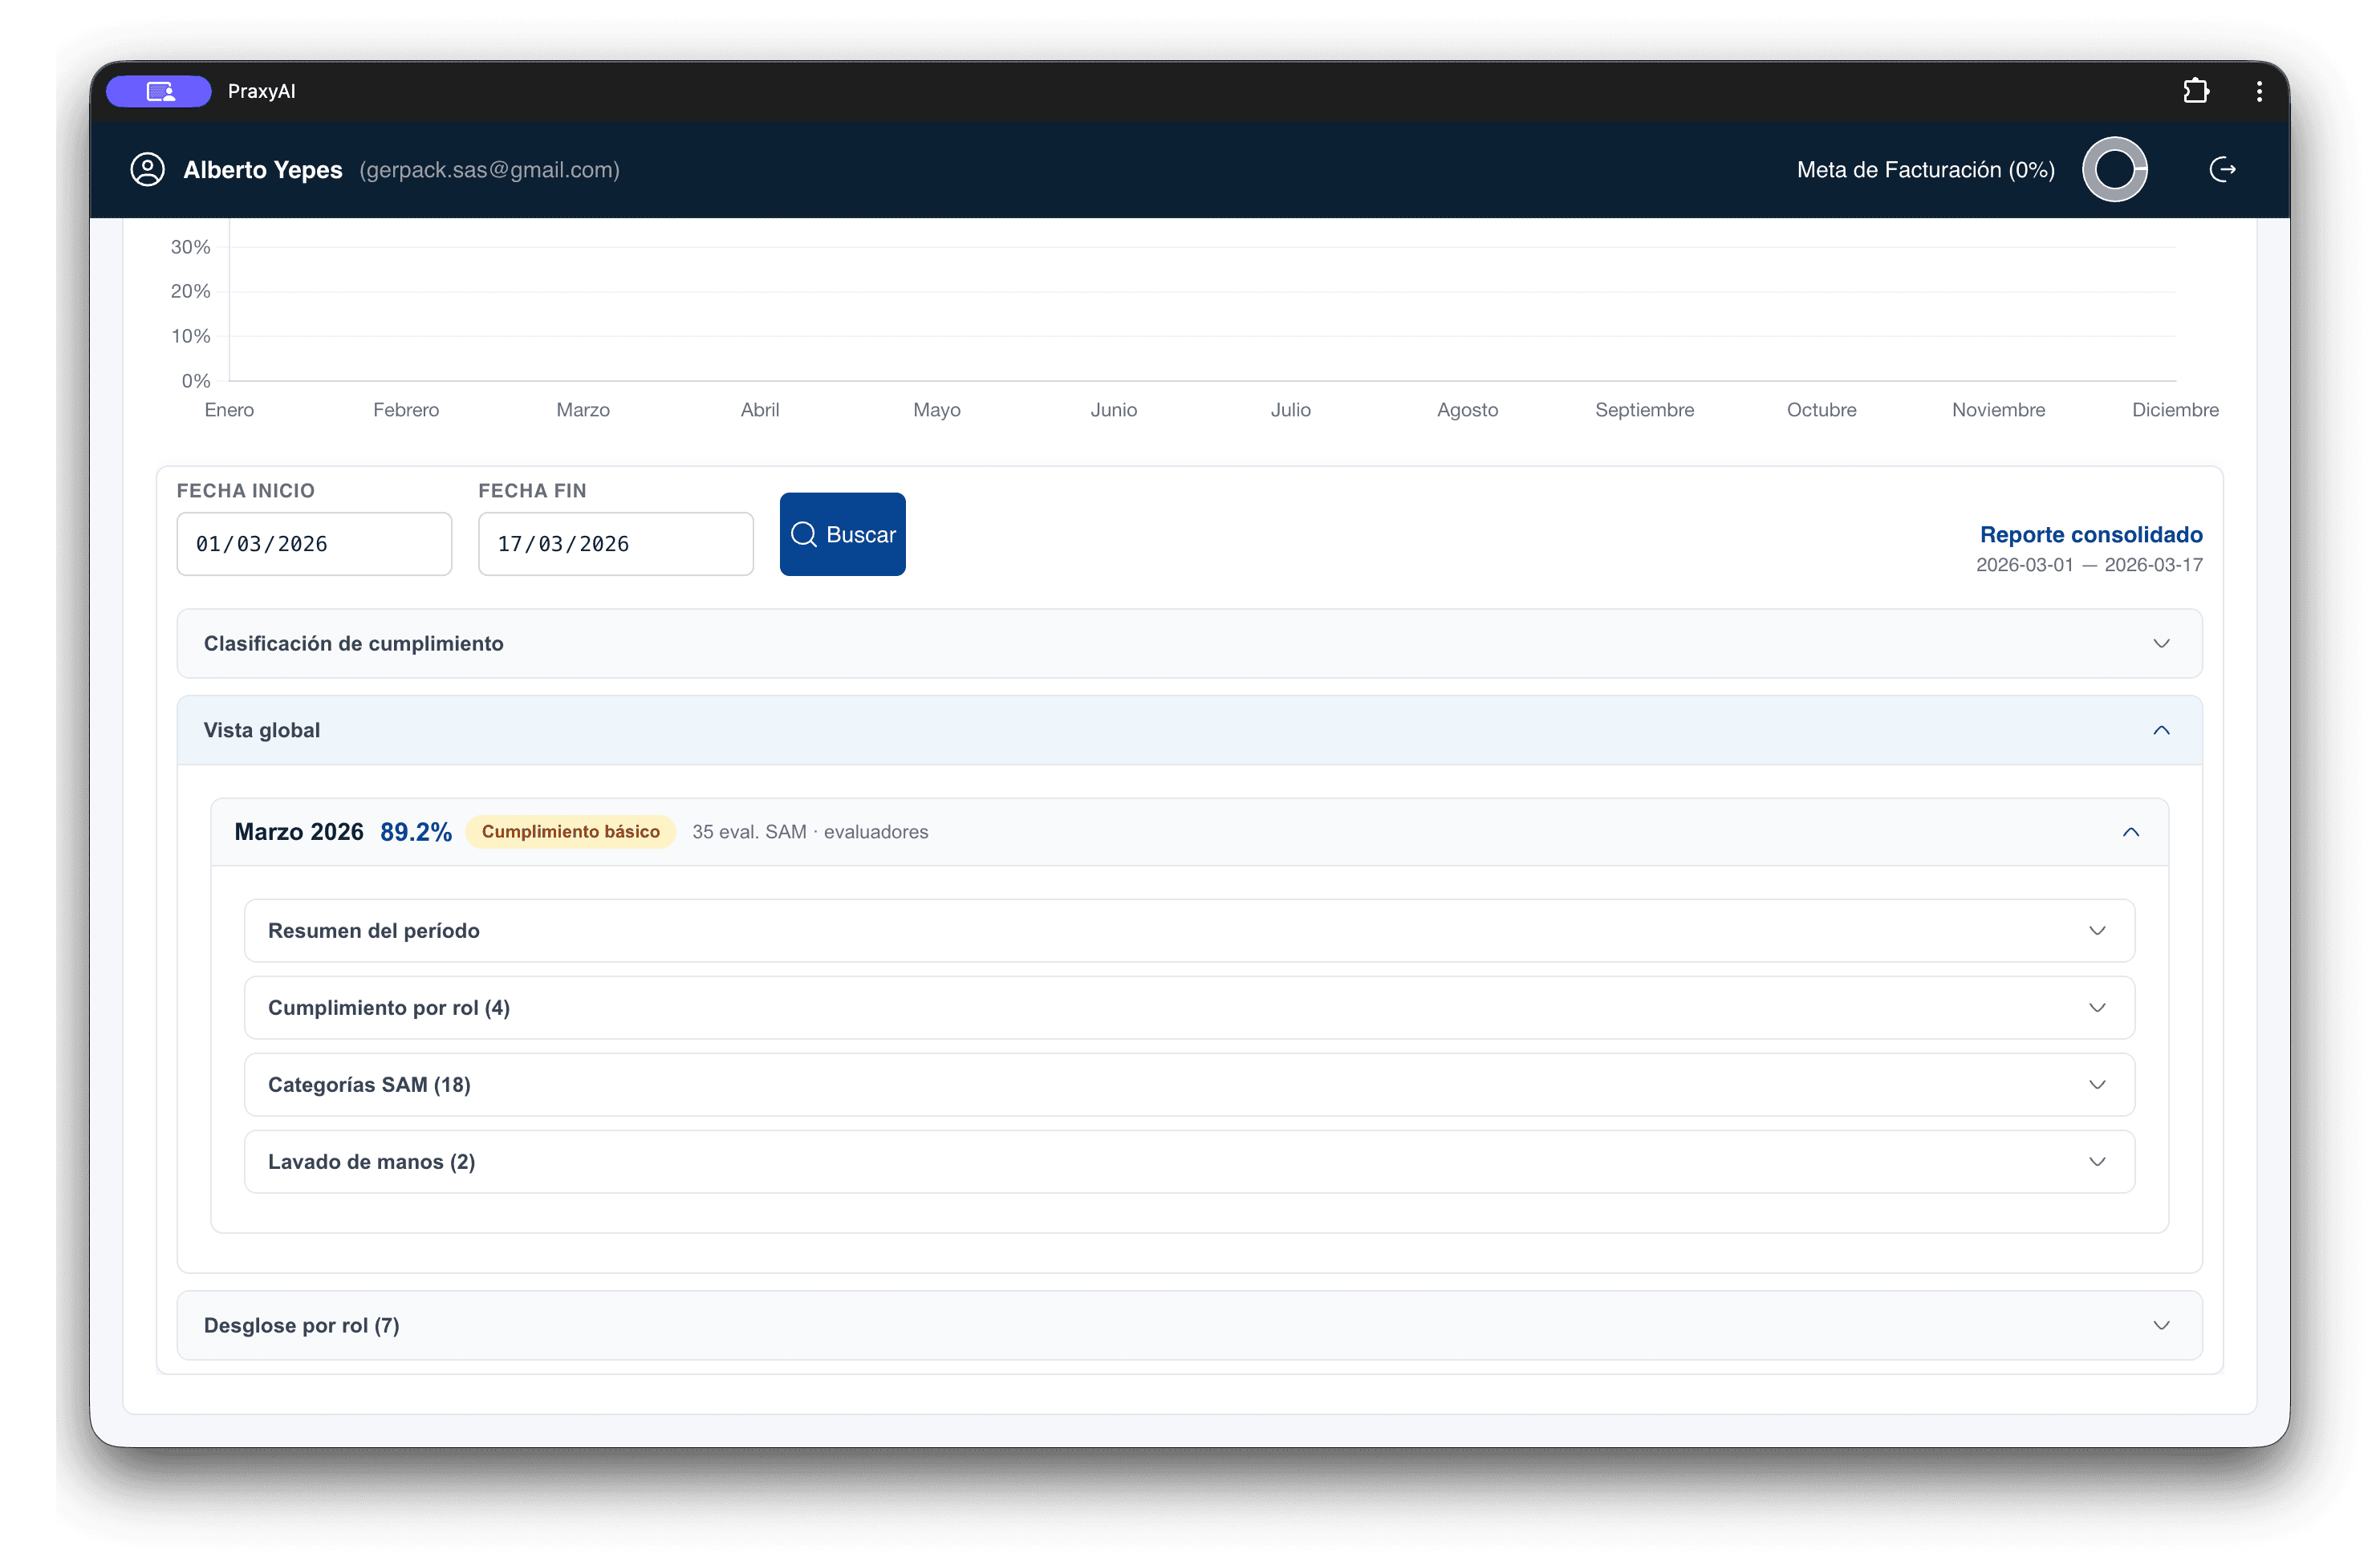
Brings hand hygiene into the same quality reading. You see the SAM average versus handwashing and the gap between them.
Clear thresholds
Adequate, basic, or insufficient: thresholds leadership and supervisors understand without reinterpreting every percentage.
Detail and filters
Filter by dates and roles, drill into each observation, and see what was met… and what remained unmet.
Executive brief with Sofia
The consolidated report summarizes the period: overall average, compliance by category, and management insights. When you need narrative, Sofia translates those numbers: where the model is strong, where it fails, and what to prioritize. The value: measurable quality, not declarative. Less gut feel, more evidence… and a clinic that proves patient care is audited too.